Thursday, July 16, 2015

A small piece of good news

To go with all the uncertanty about Ibrance and my neutrophils, I did get a small piece of good news Tuesday (sorry I didn't get it online faster!)--I got back my tumor marker number from Friday's blood draw and (drumroll...) it's a little lower than it was a month ago!

It's been going up steadily at least since April, but the July number is back to where it was in May:


These things tend to fluctuate, so the scans in August and more tumor markers to (hopefully!) show a downward trend (and not just point) will be more meaningful.  But any trend has to start somewhere, right?

It may be a trend or it may be a blip, but at least it's a relief and I'm going to enjoy it!

Next up?  More blood tests to see if those neutrophils can be peer pressured into going the right way, too (come on, neutrophils, all the cool kids are trending the right way, what's the matter? won't your mommy let you....).


Monday, July 13, 2015

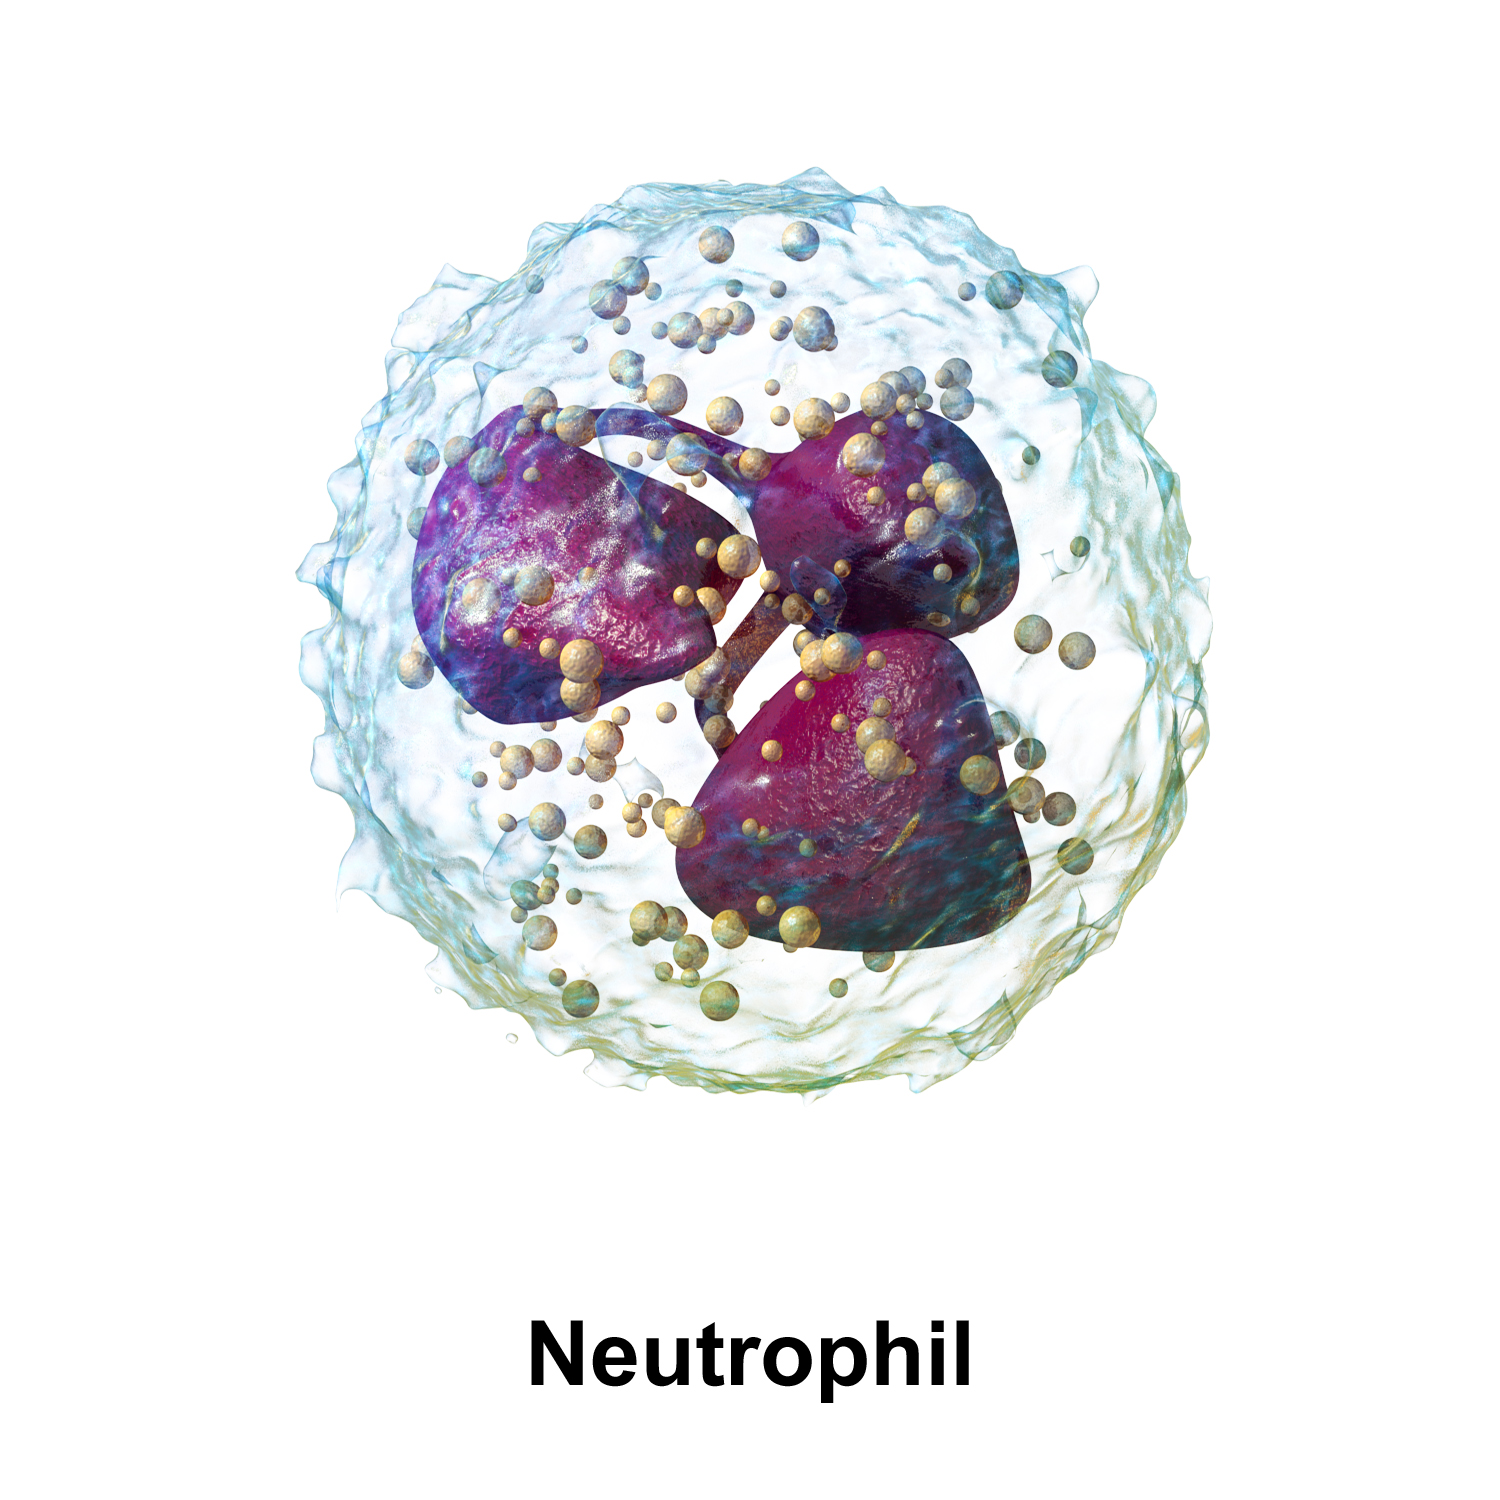
And again with the neutrophils

Another image of a neutrophil, this one from
http://www.tentrillioncellhuman.com/tag/blood/
I wrote this on Friday but was away with out internet and never got it posted, so "today" and "now" kinds of are Friday--days go by so quickly sometimes! 

I'm back in oncology for my monthly visit and again my Neutrophils are too low to continue.  Sigh.

So I'm off the 100mg, more bloodwork in a week, and hopefully starting again after that on the 75mg dose.

It's so frustrating!

I'm getting the feeling from my oncologist that I'm getting into the area where there are questions about whether the lower dose and the ratio of time off vs. time on are pushing out some of the potential benefits Ibrance would otherwise provide.

I have a CT scan scheduled for next month.  No bone scan unless the CT results show the additional info would be useful.  I'm not sure what that means, but I'm guessing it's a sign that the liver mets are the focus right now rather than the bone ones, but I could be wrong.  The CT (and possible bone scan) will be the key to deciding whether or not we keep on with the Ibrance or give up its neutrophil slaying mean little ghost and move on to different drugs.

Of course, if the scans are good despite all the time off and lowered doses, that would be great.  But at this point it's an "if" and not a "when".  

Ok, it was never a "when" and always and "if" but the "if" just seems a bit bigger right now.

But the first rule of business is to grow back these poor beleaguered neutrophils.

I've written before about trying to "read" my healthcare providers.  Trying to catch not just what they say but what it "means"--and the fact that I'm only right about 50% of the time doesn't even deter me from continuing to do it over and over again.  It's a compulsion, I guess.  My "reading" today makes me think my oncologist would be surprised if the scans were great.  Happy, sure, but still surprised.  

I agree with her recommendation to give the Ibrance another round (or however much of a round of Ibrance is under my belt after I get on those 75mgs by the time my scan appointment comes around) and then take a look then at what's going on.  I'm just saying I don't think it will be a great surprise if any major benefit Ibrance might have given me may have been tanked by my neutrophils inability to tolerate Ibrance.

And if that's the case, we move on to the next thing and hope it's the great big wonderful success we're looking for.  A.k.a. be pretty much as we'd hoped Ibrance would be.

Still, I feel great, so there is that.  I don't have an discernible symptoms from those missing neutrophils.  A few small side effects, some fleeting aches that may be cancer in the bones or may be the bones healing from the cancer (see, I can't even read me, much less other people, sheesh! no idea why I still keep trying to do that), but nothing I would pay much attention to if it hadn't been for the Ibrance/blood tests/cancer making me look).  

And, for all we know, Ibrance could be doing the trick and we just need to get those scans to know it.

So I wait to grow neutrophils, I wait for tumor markers, I wait for the scans, and I keep trying to distract myself with a beautiful summer.  And so it goes.

Monday, June 22, 2015

1250

Source: https://commons.m.wikimedia.org/wiki/
File: Team_Singapore_fireworks_display_
from_Singapore_Fireworks_Festival_2006.jpg
It's a typical Monday evening for me, rushed between getting home from work, walking, dinner, family, and life, but I wanted to pop in for a second and let you all know that I got a call from the hospital today that my latest blood test showed my neutrophils are up to 1250 (this after being down to the 600's the week before).

This means as of this evening I am back on Ibrance!

After 17 days off, I'm back in the game.

Fingers crossed that these lower 100mg capsules are a little easier on my blood cells.  And fingers double-triple crossed that the hits my blood cells have been taking are mirrored by some serious big hits on my cancer cells.  Because that would be awesome.


Saturday, June 6, 2015

Neutrophils and an Ibrance Break

The protocol with Ibrance is to go in and have your blood counts tested twice a cycle for the first few cycles to make sure your blood cells (white, red, platelets) remain at safe levels.  This is because the CDK4/6 inhibiting action of Ibrance that's supposed to help slow the cancer's evolution can also slow down blood cell production.

So, per protocol, yesterday I had my blood counts checked and I saw my oncologist.

I didn't get horrible news, but it wasn't really good news, either.

It turns out my neutrophils really don't appreciate having their CDK4/6 inhibited.  They've dropped down to an Absolute Neutrophil Count (ANC) of 810. 

Normal ANC is, according to my lab reports, generally between 1400 and 6600 ANC.  Throughout 2014, my ANC remained in the 3000 range, so 810 is not normal in general or for me in particular.  And for Ibrance, anything lower than 1000 is considered too low to continue as planned.

Neutrophils are a kind of white blood cell that, according to Wikipedia, "form an essential part of the innate immune system." So they're not really something to get too careless about.


My oncologist showed me the protocol Pfizer has issued for Ibrance.  Per their guidelines for ANC between 1000 and 500, I am off of Ibrance for at least a week, possibly longer, until I can grow back enough neutrophils to be back up at a safer level.

Plus, when they do go back up, I'm not going to be allowed back on the 125mg dose of Ibrance I was taking.  I'll start back on 100mg and see how that goes. 

I asked my oncologist the obvious question: will this reduce effectiveness? She says that in the clinical trial about 25% of patients needed to lower the dose for one reason or another but it didn't seem to correlate to a direct drop in progression free survival (or something like that, I was honestly still a little distracted by neutrophil numbers).  I know it wasn't exactly, "of course not!" but it also wasn't "of course it does!" So at least that's something.

I also just yesterday read about a woman on Ibrance who had to take a full month off with low counts and, after that, was taking the 100mg dose and still had a nice stable scan.  I know, I hear you, the plural of "anecdote" isn't "data", but still, it's not a bad sign.

Does it make me a little nervous to be off of Ibrance before I even finish my second cycle?  Yes, it does.  Does it make me a little nervous to be on a reduced dose of Ibrance when I get back on it?  Yes, that, too. 

But, on the other hand, I am still fighting the after-effects of my second cold in 6 weeks, so having more neutrophils does have some appeal.  And if taking a lower dose can get rid of the sore nose-throat-windpipe side effects I've been be having, that would be a good thing.  And maybe the headrushes when I stand up and the general fatigue that's been hitting me in the afternoons, I wouldn't mind getting rid of those, too.


But, none of these other side effects seem like deal breakers for me if the drug is working.  In fact, if I wasn't taking Ibrance and being aware of things like that, I'm not sure I'd really give them much more thought beyond a, "hmm, that's odd," sort of response. Probably followed by the same strong coffee to get through the day and early bedtime for the fatigue.  Same as I've been resorting to lately.  But, it's probably not something I'd have been super concerned about without Ibrance.

Of course, bacterial and fungal infections, inability to fight off the naturally occurring bacteria in your mouth and digestive tract, septic shock, and things like that are serious deal breakers.  And that's what is increasingly likely if my neutrophils continue to drop and head down past the 500 ANC range.*  Which is, of course, why Ibrance is off the table until I can grow back some neutrophils.

Because it doesn't really make much sense to take Ibrance to try and hold off death from cancer just to turn around and die from septic shock.   That's pretty obvious.

So I'm not an Ibrance drop out (hooray, me!) but I am, more or less, in Ibrance detention hall.  And no idea for how long.  But with any luck, when I go back to retest next week, I'll have some better numbers and be ready to get back into the Ibrance club.

In the meantime, if you need me, I'll be the one sitting over there in the corner studiously working on growing  neutrophils.

___
* I don't really know what the protocol is if my nuetrophils were to get below 500, but my guess is there'd be some Neulasta injections or other interventions.  The first step is to do what we're doing: stop killing those neutrophils.  But if it got worse anyway, my guess is they'd take steps. I do know they're watching me and aren't going to just sit back and watch sepsis set in, so don't be concerned about that.


Sunday, May 31, 2015

A little bit of housekeeping

Two quick things: a correction and an option.

The correction: On my last post, I mentioned that the results of the PALOMA-3 with news on whether Ibrance is helpful in Overall Survival (how long people live) in addition to Progression Free Survival (how long till the cancer evolves around it and grows again) are expected to be presented at ASCO this weekend.

This is not actually true! 

It's sort of half true, but that doesn't count for much.  The actual truth is that the results of PALOMA-3 will be (or have been) presented at ASCO this weekend, but those are aren't Overall Survival (OS) for Ibrance and letrozole.  They're actually Progression Free Survival (PFS) of Ibrance and Faslodex--the results are very good, and Ibrance more than doubled PFS over Faslodex alone, from a median of  3.8 months to 9.2 months, which is, as I understand it, an almost unheard level of improvement in cancer drug development.  It's similar to the improvement found with Ibrance and letrozole over letrozole alone and all points to Ibrance being a really big deal in the treatment of hormone receptor positive metastatic breast cancer.  A huge big deal.

For me, personally, it's probably not that useful since I've already flunked out of Faslodex, but it will be big for a lot of women in the future, so that's really good news.

The study results I was thinking of about Overall Survival with Ibrance and Letrozole are actually Phase III of the PALOMA-2 trial (not phase II of the PALOMA-3 trial, but maybe you can see where I went wrong there!) are due out in October.  And I'm still anxiously awaiting those, though even more anxiously awaiting getting to the my next scans and seeing how Ibrance and Letrozole are working for me!


And the option:  I've just made a Facebook page for this blog for people who like to use Facebook to follow blogs.  If that's you, here you go!  You can go directly to www.facebook.com/mepluscancer or click the Facebook icon to the top left, and (either way) "like" the page.

If that's not you, or you just don't want to follow this one there, no worries.  And I promise this is the last I'll mention it.  And there will be no "give-aways and please, please, please like it" posts.  Because I don't like those.  And also, this is a blog about metastatic cancer so what exactly would I give away, anyhow? (Can you see it now?  300th person to like it gets an empty bottle of letrozole, 400th gets an Ativan info sheet and an empty bottle of Ibrance--whoot!)


Friday, May 29, 2015

The most wonderful time of the year

Today is the first day of the 2015 Annual Meeting of the American Society of Clinical Oncology.

It's a time when all kinds of cancer researchers, cancer drug companies, and cancer healthcare professionals present papers and reports on their research and clinical trials, and already some releases are hitting the mainstream news.

There are other meetings throughout the year that have similar presentations--the results of the PALOMA-2 trial were released at last year's American Association of Cancer Research meeting, which resulted in early FDA approval of palbociclib/Ibrance, which resulted in me being able to take it now--but advance press on this one has been really promising.

And results on PALOMA-3 with news on whether Ibrance is helpful in Overall Survival (how long people live) in addition to Progression Free Survival (how long till the cancer evolves around it and grows again) are expected to be presented.  Obviously I'm very interested in news about that one!

A lot of the research they will announce is still years away from being usable as cancer therapy, but it's progress and a sign that there are new things coming.  And, hopefully, there will be something good coming to take the place once my cancer evolves around Ibrance.  Maybe even something more permanant.

My brother sent me a link to one article based on brand new research with the subject: "Hold the line!  Help is on the way!"

I love that!  That's the plan, that's the goal, hold the line long enough for the next army to arrive.  

And this weekend, we should get a first look at some of the armies making their way to my battlefield.  And God willing, there will be at least a few butt-kicking regiments all geared up and getting ready jump on in and save the day.

Saturday, May 23, 2015

Numbers that may or may not mean something

M.C. Escher - No. 45 Angels and Devils
Have you ever watched those videos where an artist starts drawing something and at first you have no idea what it's supposed to be but at the end, with those final last strokes--presto!--suddenly it all comes together and turns into something?  They used to do a lot of those on Sesame Street with the voice-over kids guessing all the while at what it would finally turn out to be.

Health care is like that, too.   

Sometimes there's a lump or bump, maybe a random, fleeting pain.  You don't think that much of it at the time, but when it gets worse or other things happen, you get a diagnosis and in hindsight you can see how it all fit together.  Pieces of the whole.

I'm thinking of that because my tumor markers have gone up.

Long time readers and those of you also involved with cancer will know that tumor markers are something some cancer tumors give off into the blood.  They aren't present for everyone with breast cancer and they aren't 100% reliable even if they are present, but I have them and they seem to be pretty reliable, as verified by the CT and bone scans (more about tumor markers here).  And, basically, the more active the cancer, and the more cancer there is, the higher the tumor markers are.

And mine have gone up a lot since we last tested them in early April.

I'll admit, when I first saw the high number, higher than I've ever seen it before, I panicked.  Damn you, Ibrance, you stupid punk, not even worth a month? Really?!?

But then I started thinking.  And the real truth is that I have no idea what it means.

It's true, in general, high tumor markers are bad, but a few things I was thinking of:
  1. Anti-hormonals like Faslodex and Letrozole (with or without Ibrance) can take a while to make a difference.  That's why if it's a crisis, they go for radiation or chemo, not anti-hormonals.  The problem for me is that I don't know what "a while" means here and I don't really know what's supposed to happen in the meantime.
  2. I've read that sometimes anti-hormonals can cause tumor "flares" when you start taking them, where the cancer activity ramps up sharply as the tumor starves for estrogen, but after the flare, the anti-hormonals start to make a difference.  But it isn't true in all cases and I don't know if it's true at all when you switch from one type of anti-hormonal (like Faslodex, an estrogen receptor downregulator) to another kind (like Letrozole, an aromatase inhibitor).  So these numbers could be a sign of a flare indicating effectiveness.  Or they could be a sign that the cancer is just plain growing, indicating ineffectiveness.   Who can say?
  3. I know what my tumor markers were in early-April and I know where they were 6 weeks later, but the thing is I have no idea what they were doing in the meantime.  For all we know, they could have gone up a lot higher between the two points.  For all we know, this newest high number could actually be a lovely, Ibrance and Letrozole led drop from whatever even higher point they were at in between. Really I have absolutely no idea.
There's a reason I don't practice medicine.  Clearly, I have no idea whatsoever what I'm doing.  And maybe some people really do have that Earth-Mother-Goddess ability to "know their bodies" and listen to some sort of soft, sweet voice of confident intuition telling them what's going on, allowing them the supernatural ability to "know their bodies best."  I think that would be really cool, but I wouldn't know for sure because I've never, ever had such a thing happen to me.  Ever.

But I did come up with one good thought of my very own (or maybe that's my soft, sweet voice of confident intuition finally weighing in, but probably not).  I don't practice medicine, but I know someone who does.

So I went back onto the new Electronic Medical Record site where I saw the high tumor marker number and sent a message to my oncologist asking her what, if anything, we were supposed to make of this number.

And she told me, basically, that it's just too soon to tell.  It's too soon to know if the drugs are working, too soon to know which piece of which picture this one is going to turn out to be.  She's not worried right now and it's no reason to switch drugs right now.  Because, right now, it's just too soon to know.

So this picture could end up being "Dawn of Utopia" or it could end up being "End of an Empire," but right now, no one but God himself can tell where this one's going.

The good news is it isn't bad news. The bad news is it isn't good news.  And beyond that we just need  to wait and see what kind of news it will turn out to be.